
研究一
中文标题:
OPTIMUM:一项随机Ⅱ期研究,评估奥拉帕利(Ola)联合或不联合度伐利尤单抗(Durva)维持治疗DDR基因突变型晚期胆道癌(aBTC)的疗效
英文标题:
OPTIMUM: A randomized phase 2 study of maintenance olaparib (Ola) with or without durvalumab (Durva) in DDR gene-mutated advanced biliary tract cancer (aBTC)
Changhoon Yoo (Seoul, Republic of Korea, Songpa-gu)
摘要号:
LBA22
研究背景
含铂化疗是aBTC患者的标准治疗方案;然而,目前尚无疾病控制后的维持治疗策略得到验证。aBTC患者存在DNA损伤修复(DDR)基因突变,PARP抑制剂维持治疗可能改善该人群的生存率。
研究方法
OPTIMUM是一项随机、开放标签、非对照Ⅱ期临床试验。入组患者需满足:aBTC、ECOG PS评分为0~1分、携带至少1种预设的体细胞或胚系DDR基因突变;接受一线含铂方案治疗≥16周后疾病未发生进展。患者按1:1比例随机分至A组(奥拉帕利300 mg,每日2次+度伐利尤单抗1500 mg静脉输注,每4周1次)或B组(奥拉帕利300 mg,每日2次)。主要研究终点为全分析集(FAS)的6个月无进展生存(PFS)率;共需入组62例患者,以验证6个月PFS率由历史数据48.0%提升至69.3%(风险比HR=0.5;单侧α=0.05,检验效能80%)(图1)。
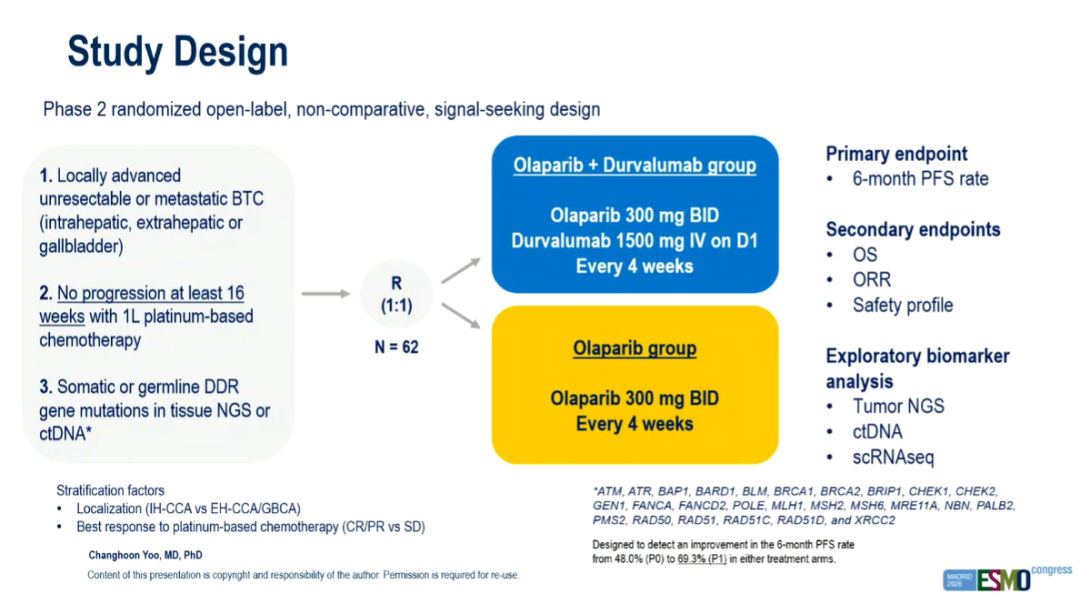
图1. OPTIMUM研究设计
研究结果
2022年4月至2026年2月,共入组63例患者,61例患者纳入FAS(A组32例;B组29例)。两组基线特征均衡。最常见DDR基因突变为ATM(34%)、BRCA2(25%)及BAP1(25%)。A组6个PFS率为62.5%(95%CI:46.8~74.7),B组为62.1%(95%CI:45.5~74.9)(图2)。FAS人群2年总生存率为40.1%(95%CI:28.0~51.9)(图3)。核心同源重组缺陷(cHRD)亚组(18例,占30%)的中位PFS(20.5个月 vs. 7.4个月,P=0.008)及OS(尚未达到 vs. 16.5个月,P=0.007)均显著优于其他亚组。研究治疗时ctDNA中较高的变异等位基因频率(VAF)与PFS和OS呈负相关。奥拉帕利联合或不联合度伐利尤单抗,未出现新的安全性信号。
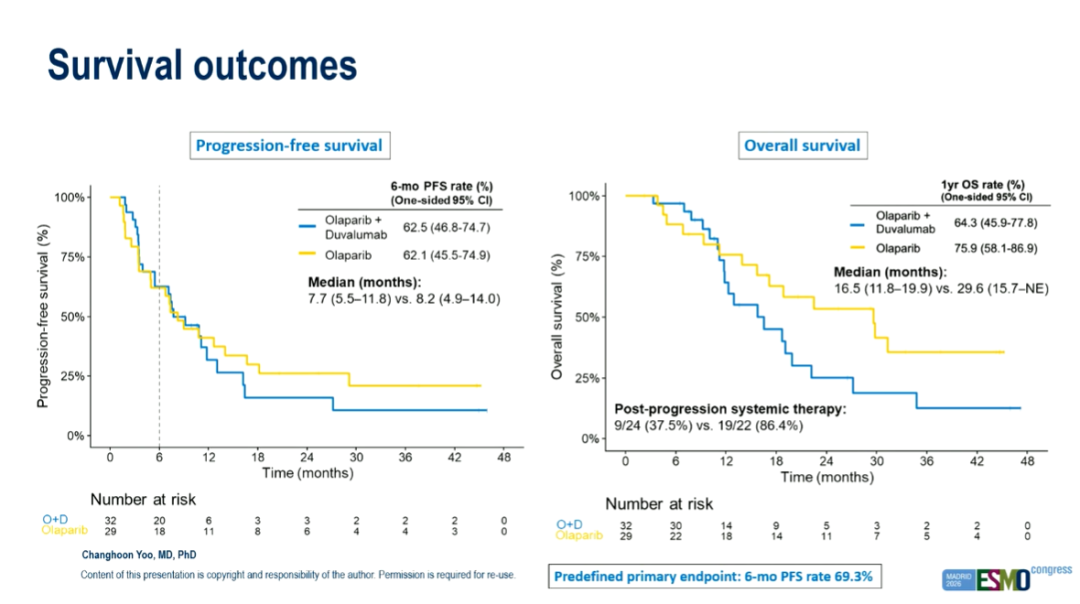
图2. PFS与OS
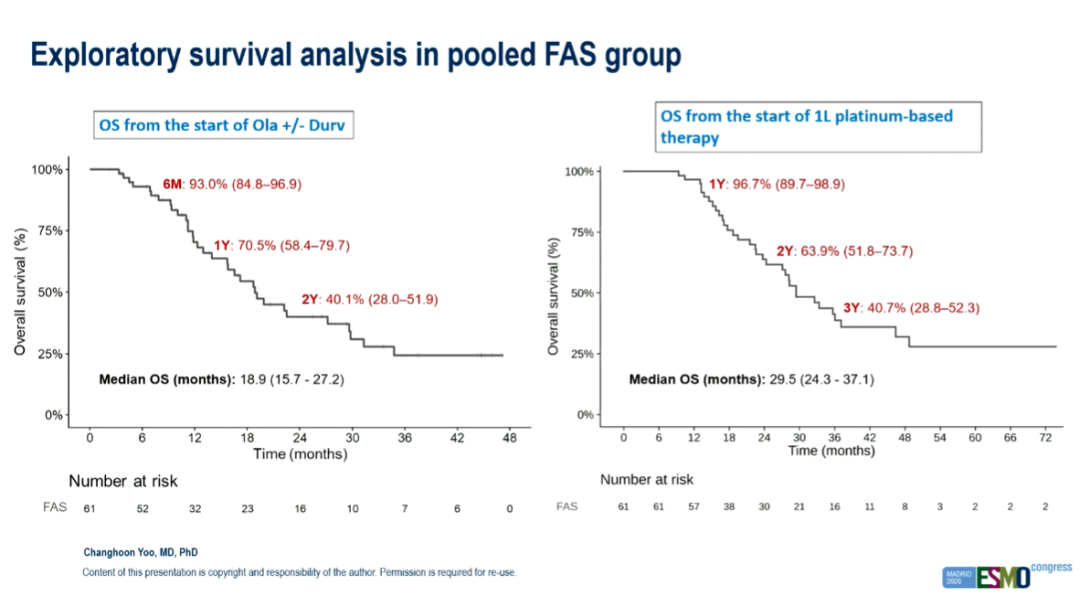
图3. FAS人群的探索性生存分析
研究结论
本研究结果提示,cHRD定义的DDR突变aBTC,可从PARP抑制剂维持治疗中获得持久获益,支持进一步开发针对aBTC的HRD靶向治疗方案[1]。
研究二
中文标题:吉西他滨联合顺铂、度伐利尤单抗(MEDI4736)和曲麦利尤单抗治疗肝内胆管癌的Ⅱ期研究(NeoTreme)
英文标题:Phase 2 study of preoperative gemcitabine plus cisplatin with durvalumab (MEDI4736) and tremelimumab in intrahepatic cholangiocarcinoma (NeoTreme)
讲者:Markus Moehler (Mainz, Germany)
摘要号:471P
研究背景
手术切除是肝内胆管癌(iCCA)根治性治疗的金标准。然而,尽管辅助治疗策略不断优化,大多数患者仍会出现快速复发。近年来,免疫联合疗法的出现为术前全身治疗提供了一种有前景的策略。
研究方法
本研究为一项前瞻性、多中心、单臂、Ⅱ期可行性临床试验,入组经组织学确诊、适合接受手术切除的初治iCCA患者。患者在手术切除前接受新辅助化疗联合免疫治疗(吉西他滨1000 mg/m2,顺铂25 mg/m2,于每周期第1、8天给药;度伐利尤单抗1500 mg,于21天周期的第1天给药;以及在第一个周期的第1天单次给予曲麦利尤单抗300 mg),共三个周期。主要终点为R0/R1切除率(图4)。本文报告所有接受至少1剂研究药物的入组患者的中期分析数据。
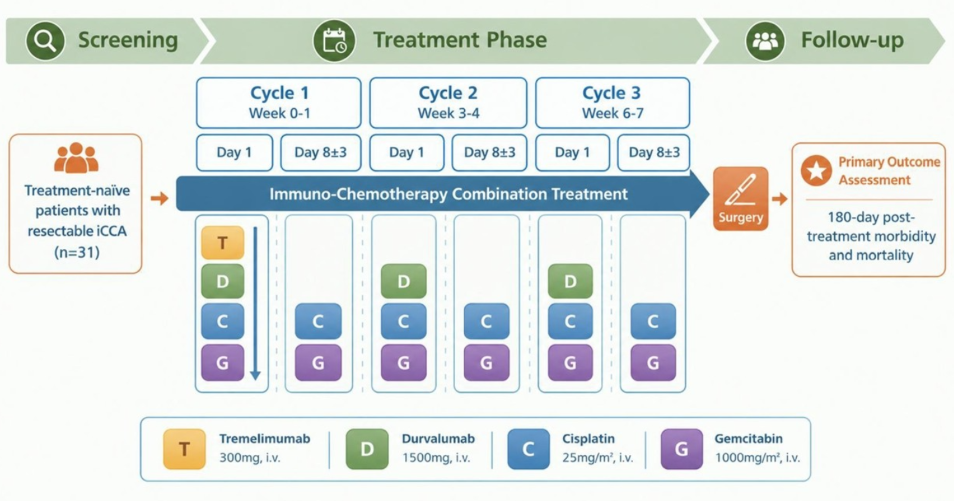
图4. 研究设计
研究结果
共有31例患者接受了至少一剂研究药物。研究人群包括18例女性(58%)和13例男性(42%),中位年龄为62岁(四分位间距IQR,56~74岁)。所有患者的中位随访时间为173天(IQR,146~182天)。共有27例患者接受根治性手术切除,其中26例(84%)达到R0/R1切除(图5)。所有患者均发生至少1起不良事件。共有8例患者(26%)发生16起治疗相关严重不良事件,包括中性粒细胞减少伴发热(4例)、感染/脓毒症(3例)、腹泻(2例)、免疫相关性结肠炎(2例)、免疫相关性肝炎(2例)、免疫相关性心肌炎(1例)和免疫相关性后葡萄膜炎(1例)。
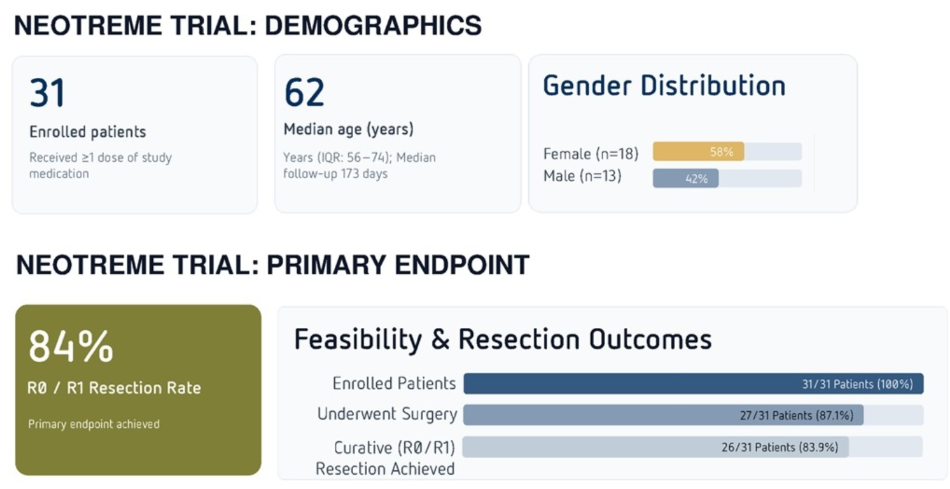
图5. 研究结果
研究结论
对于iCCA,手术切除前采用吉西他滨、顺铂、度伐利尤单抗和曲麦利尤单抗进行新辅助化疗免疫治疗,值得在后续的随机对照Ⅱb/Ⅲ期试验中进行进一步研究[2]。
参考文献:[1] Changhoon Yoo, et al. 2026 ESMO. Abstract LBA22.[2] Markus Moehler , et al. Lancet. 2026 ESMO. Abstract 471P.
LBA22摘要原文:
OPTIMUM: A randomized phase 2 study of maintenance olaparib (Ola) with or without durvalumab (Durva) in DDR gene-mutated advanced biliary tract cancer (aBTC)
BACKGROUND:
Platinum-containing therapy is standard of care for pts with aBTC; however, no maintenance strategy has been validated following disease control. DNA damage repair (DDR) gene mutations are identified in pts with aBTC and PARP inhibitor maintenance may improve survival in this population.
METHODS:
OPTIMUM is a randomized, open-label, non-comparative, phase 2 trial. Eligible pts had aBTC, ECOG PS 0–1, at least one predefined somatic or germline DDR gene mutation, and no disease progression after ≥16 weeks of 1L platinum-based therapy. Pts were randomized 1:1 to Arm A (Ola 300 mg BID + Durva 1,500 mg IV Q4W) or Arm B (Ola 300 mg BID). The primary endpoint was 6-month PFS rate in the Full Analysis Set (FAS), and 62 patients were required to detect its improvement from a historical 48.0% to 69.3% (HR 0.5; one-sided α=0.05, power 80%).
RESULTS:
Between April 2022 and February 2026, 63 pts were enrolled, and 61 pts were included in the FAS (Arm A: n=32; Arm B: n=29). Baseline characteristics were well balanced between arms. The most frequent DDR alterations were ATM (34%), BRCA2 (25%) and BAP1 (25%). The 6-month PFS rate was 62.5% (95% CI, 46.8–74.7) in Arm A and 62.1% (45.5–74.9) in Arm B. Two-year OS rate in overall FAS was 40.1% (28.0–51.9). The core homologous recombination deficiency (cHRD) group (n=18, 30%) was significantly associated with better median PFS (20.5 vs. 7.4 mo, P=0.008) and OS (not reached vs. 16.5 mo, P=0.007) compared to others. Higher VAF in ctDNA at the time of study treatment showed negative correlation with PFS and OS. There was no new safety profile of Ola +/- Durva.
CONCLUSIONS:
Our findings suggest that a cHRD-defined DDR-mutated aBTC derives durable benefit from PARP inhibitor maintenance, supporting further development of HRD-targeted therapy in aBTC.
471P摘要原文:
Phase 2 study of preoperative gemcitabine plus cisplatin with durvalumab (MEDI4736) and tremelimumab in intrahepatic cholangiocarcinoma (NeoTreme)
BACKGROUND:
Surgical resection is the gold standard in curative stages of intrahepatic cholangiocarcinoma (iCCA). However, despite improved adjuvant strategies, rapid recurrence is observed in majority of patients. Recent advent in immunotherapy combinations supports the use of systemic treatment as a promising strategy in pre-operative settings.
METHODS:
This prospective, multicenter, single-arm, feasibility phase II trial was conducted for treatment-naïve patients with histologically confirmed iCCA eligible for surgical resection. Patients received neoadjuvant chemoimmunotherapy (gemcitabine 1000 mg/m2, cisplatin 25 mg/m2 on days 1 and 8 in combination with durvalumab 1500mg on days 1 of a 21-day cycle and a single dose of tremelimumab of 300mg on day 1 of first cycle) for a total of three cycles prior resection. Primary endpoint was rate of R0/R1 resections. Here presented data is an interim-analysis of all enrolled patients who received at least one dose of study medication.
RESULTS:
A total of 31 patients received at least one dose of study medication. Study population included 18 female (58%) and 13 male patients (42%) with a median age of 62 (IQR, 56–74). Median follow-up for all patients was 173 days (IQR, 146–182). Overall, 27 patients underwent curative-intent surgical resection with an R0/R1 resection in 26 patients (84%). All patients experienced at least one adverse event. Overall, 16 treatment-related serious adverse events occurred in 8 patients (26%) including neutropenic fever (4), infections/sepsis (3), diarrhea (2), immune-related (ir) colitis (2), ir-hepatitis (2), ir-myocarditis (1) and ir-posterior uveitis (1).
CONCLUSIONS:
Neoadjuvant chemoimmunotherapy with gemcitabine, cisplatin, durvalumab and tremelimumab prior to resection of intrahepatic cholangiocarcinoma warrants further investigation in a subsequent randomized controlled phase IIb/III trial.
声明:本文仅供医疗卫生专业人士了解最新医药资讯参考使用,不代表本平台观点。该等信息不能以任何方式取代专业的医疗指导,也不应被视为诊疗建议,如果该信息被用于资讯以外的目的,本站及作者不承担相关责任。